What This Measure Shows
The anion gap is a useful way to assess ion balance and help identify sources of acidic imbalance. It is not a direct measurement of a single substance in blood chemistry. Instead, it is a calculated value that represents the difference between commonly measured positive and negative ions in the plasma.
An anion gap calculator helps medical users quickly check whether there may be extra unmeasured anions present. These may appear in conditions that disrupt acid-base balance, especially when the blood shows a pattern consistent with metabolic acid-base abnormality.
In simple terms, the anion gap compares measured sodium against measured chloride and bicarbonate. Because those three values are usually included in an chemistry panel, the calculation is easy to apply in routine care. The result can support clinical assessment of an electrolyte imbalance, especially when a patient has decreased bicarbonate or other signs of acid retention.
Although the anion gap is often taught as a standalone concept, it is most useful when interpreted alongside other lab values, symptoms, and the larger pattern of the blood chemistry. A normal result does not always rule out disease, and an abnormal result does not stand alone as a diagnosis. It is a diagnostic tool that helps anion gap calculation narrow the possibilities.
How to Use an Anion Gap Calculator with Serum Sodium
A trustworthy anion gap calculator generally needs three numbers: serum sodium, serum chloride, and serum bicarbonate. These values are commonly reported as part of a standard metabolic panel or a similar electrolyte panel. The calculator then runs the same arithmetic a clinician would use manually.
Using the calculator is straightforward:
- Enter the serum sodium level. Enter the serum chloride value. Provide the serum bicarbonate value. Check the output and contrast it with the normal reference range.
As serum sodium frames the formula, the calculator shows the balance between major measured cations and anions. A change in sodium, chloride, or bicarbonate can shift the result, which is why the calculator is valuable for acid base interpretation.
As an example, a patient with a normal sodium level but a reduced bicarbonate and increased chloride may still have a normal anion gap. Another patient with reduced bicarbonate and no compensatory chloride rise may have a high anion gap. The calculator helps reveal that pattern efficiently.
When reviewing the result, consider whether the numbers fit the broader clinical picture. If the patient has vomiting, dehydration, diabetes, kidney disease, or suspected poisoning, the calculated gap becomes more informative. The same is true when comparing serial values over time, since shifting electrolytes can show whether a metabolic state is getting better or declining.
Anion Gap Equation and Stepwise Calculation
The usual anion gap formula is written as:
Anion gap = sodium − (chloride + bicarbonate)
Some laboratories use slight modifications, but this version is the most widely used and is the easiest to follow for manual computing. It uses the measured sodium, chloride, and bicarbonate values from the blood.
Here is a step-by-step way to work out anion gap:
- Start with the measured sodium value. Sum the measured chloride and bicarbonate values. Take away that total from sodium. The remainder is the anion gap.
Example:
- Sodium = 140 Chloride = 104 Bicarbonate = 24
Calculation: 140 − (104 + 24) = 12
This value is usually in the expected range. In this example, the blood chemistry suggests a balanced relationship among the major measured ions.
Why does this work? Because the body contains both measured ions and unmeasured anions. The formula estimates the difference between positively charged and negatively charged components in the plasma. If the number is higher than expected, it may reflect extra acids or other unmeasured substances. That is why the anion gap is valuable in evaluating metabolic acidosis and related conditions.
Some readers prefer to think about the formula as a shortcut for identifying whether the acid-base system is balanced. If bicarbonate drops and chloride does not rise enough to offset it, the gap changes. If bicarbonate drops and chloride rises in parallel, the gap may remain normal even though there is still a major acid-base issue.
Normal Values and Interpreting Results
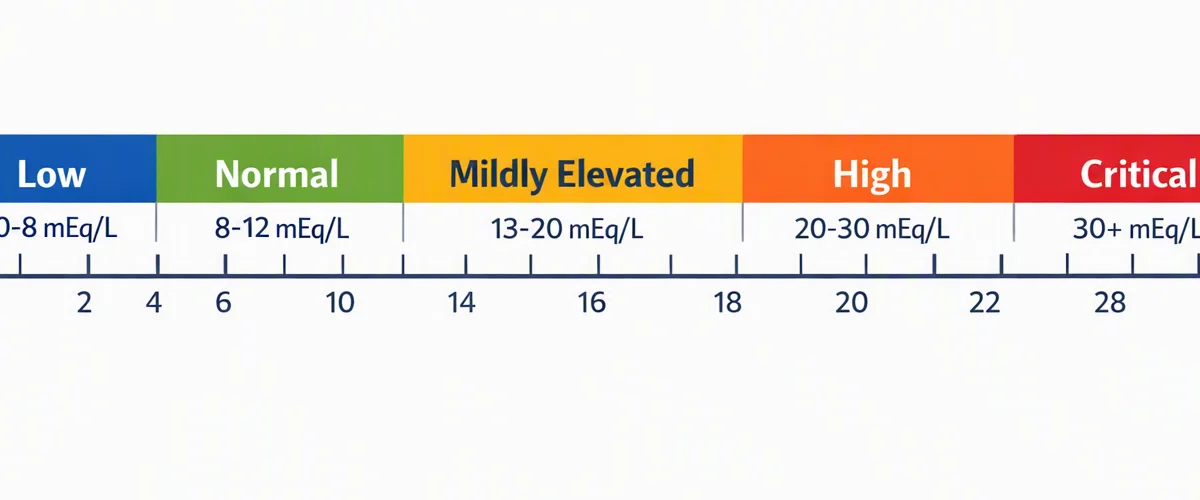
The usual anion gap is often reported within a limited normal reference range, but the precise interval depends on the laboratory method and the analyzer used. For that reason it is important to evaluate results using the reference range provided with the test instead of relying on a single universal number.
In general, a normal anion gap suggests that measured serum electrolytes are relatively stable and that there is no obvious accumulation of many unmeasured acids. Even so, normal results do not exclude every acid-base problem. A patient can still have acidosis, especially non-gap forms where chloride increases to keep the overall balance stable.
A increased anion gap suggests that extra acids or other unmeasured anions are present. This finding often points toward acidic metabolic imbalance and should prompt a more careful look at causes such as lactate, ketones, kidney dysfunction, or toxins. The result is not a diagnosis by itself, but it is a valuable clue.
Albumin also matters because it is a major unmeasured negatively charged protein in plasma. When albumin is low, the measured gap may appear less concerning than it is. This is why the raw number should be interpreted alongside albumin concentration and the patient’s overall state.
In practice, the most useful approach is to interpret results in context:
- Normal gap plus low bicarbonate may suggest a non-anion-gap acid-base issue. Low bicarbonate with a high gap points toward a anion-gap acidosis pattern. Low albumin can decrease the apparent gap and hide a true abnormality.
Revised Anion Gap and Albumin Adjustment
Because albumin plays a major role in the anion gap, hypoalbuminemia can mask a true elevation. Under those circumstances, a corrected anion gap is more useful than the unadjusted value. The purpose is to correct for albumin so the result better reflects the patient’s actual acid-base state.
There are several albumin correction approaches, but the key idea is straightforward: lower albumin lowers the observed anion gap. If albumin is reduced, the clinician should consider a correction before concluding that the gap is normal.
A typical correction method applies a set amount to the measured gap for each decrement in albumin below normal. The exact adjustment may vary by formula, so a calculator that includes albumin can be particularly helpful. The important clinical principle is that hypoalbuminemia can mask a high anion gap.
This matters because: a patient with low albumin and elevated lactate may have a corrected value that meaningfully alters interpretation. Without adjustment, the raw anion gap can downplay the severity of the metabolic derangement.
Consider the following clinical reasoning:
- The observed gap seems normal. Albumin is decreased. Once albumin is corrected, the gap becomes elevated.
This difference can reveal hidden acidosis and support further evaluation. In other words, the corrected anion gap is not just a mathematical exercise. It is an approach to avoid missing clinically important acid-base abnormalities.
When using an anion gap calculator, always check whether it includes albumin input or provides a separate albumin correction field. If not, you may need to modify the number manually when albumin is abnormal.
Typical Causes of an Abnormal Anion Gap
An abnormal gap is usually a indicator that something is changing the body’s acid level or electrolyte profile. The leading causes of a high anion gap include lactic acidosis, ketoacidosis, renal failure, and toxins.
Lactic acidosis occurs when lactate accumulates because tissues are not using oxygen effectively or because metabolism is disrupted. This often appears in severe illness, shock, hypoperfusion, or other states of tissue hypoxia. The extra lactate acts as an unmeasured anion and elevates the gap.
Ketoacidosis develops when ketone bodies build up, commonly in diabetes but also in starvation or alcohol-related states. These ketones cause metabolic acidosis and widen the gap.
Renal failure can also cause an elevated gap because impaired kidneys do not remove acids effectively. As acids accumulate, the plasma shows more unmeasured anions and less bicarbonate.
Toxins are another important category. Certain ingestions introduce acids or acid precursors that produce a high-gap pattern. In these cases, the anion gap may provide an early warning that directs urgent evaluation.
Frequent causes for a normal anion gap with acidosis include gastrointestinal bicarbonate loss or renal anion gap tubular causes. In those cases, chloride often rises to replace lost bicarbonate, which is why the gap can remain normal despite serious illness.
Useful pattern recognition can be summarized this way:
- High anion gap: think extra acids or retained acid. Normal anion gap: suspect bicarbonate loss with compensatory chloride rise. Always check sodium, chloride, bicarbonate, and the full clinical picture.
Clinical Perspective and Acid-Base Disorders
The anion gap works best when viewed in the broader setting of acid-base imbalances. It is only one piece of the puzzle. A patient may have a metabolic alkalosis, ventilatory acidosis, or mixed condition in addition to an abnormal gap, and the overall pattern is more important than the value itself.
In metabolic base excess, bicarbonate is elevated rather than reduced, so the anion gap is not the main indicator. Still, the gap may help identify a mixed condition if a patient has both alkalosis and a hidden high-gap process.
In carbon dioxide retention, carbon dioxide retention is the main problem, not an isolated bicarbonate change from acid accumulation. However, long-standing lung disease can lead to secondary changes in bicarbonate that complicate interpretation. The anion gap can help identify or dismiss an accompanying metabolic disorder.
This is why a good interpretation of acid-base status uses more than one number. A clinician may review pH, CO2, bicarbonate, sodium, chloride, and albumin together. The anion gap then becomes a useful diagnostic tool for identifying whether the disturbance is metabolic, respiratory, or mixed.
Another helpful concept is the delta gap. This compares the rise in anion gap with the fall in bicarbonate and can suggest whether more than one metabolic process is happening at once. It is especially useful when the clinical picture does not match the expected pattern. A delta gap can reveal a hidden metabolic alkalosis or an additional non-gap acidosis alongside a high-gap disorder.
In practical terms, the anion gap supports bedside reasoning:
- Is there metabolic acidosis? Is the gap elevated or within range? Is albumin low enough to require adjustment? Do the results agree with the symptoms and other laboratory values?
Frequently Asked Questions
What is the anion gap calculator with serum sodium used to do?
This anion gap calculator using serum sodium is used to quickly determine anion gap from routine blood chemistry values. It assists in assess acid-base balance, detect possible metabolic acidosis, and identify patterns such as a high anion gap or normal anion gap. It is particularly useful when reviewing an electrolyte panel that includes sodium, chloride, and bicarbonate.
How do you calculate anion gap from sodium, chloride, and bicarbonate?
Apply the standard anion gap formula: sodium − (chloride + bicarbonate). Input the measured sodium, chloride, and bicarbonate values, then subtract the sum of chloride and bicarbonate from sodium. This yields the calculated gap, which can then be compared with the normal reference range.
What counts as a normal anion gap?
A normal anion gap depends on the laboratory’s method and reference interval, so the best answer is the range printed with the test results. In many labs, the normal reference range is relatively narrow. Always interpret the result using the lab’s reported range and the patient’s overall clinical picture, especially if albumin is abnormal.
Why is the anion gap corrected for albumin?
You correct the anion gap for albumin because low albumin can make the measured gap look falsely normal. With hypoalbuminemia, a true elevation may be hidden. A corrected anion gap gives a more accurate estimate of the acid-base state by adjusting for the loss of this major unmeasured anion. For this reason many clinicians choose to correct for albumin when interpreting results.
What does a high anion gap typically mean?
A high anion gap usually means there are extra unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and certain toxins. It often points to metabolic acidosis, but the result should always be interpreted with other laboratory values, symptoms, and the full acid-base pattern.